
فیزیولوژی پزشکی گایتون و هال؛ فیزیولوژی هوانوردی، نواحی مرتفع و فضانوردی


دعای مطالعه [ نمایش ]
بِسْمِ الله الرَّحْمنِ الرَّحیمِ
اَللّهُمَّ اَخْرِجْنى مِنْ ظُلُماتِ الْوَهْمِ
خدايا مرا بيرون آور از تاريكىهاى وهم،
وَ اَكْرِمْنى بِنُورِ الْفَهْمِ
و به نور فهم گرامى ام بدار،
اَللّهُمَّ افْتَحْ عَلَيْنا اَبْوابَ رَحْمَتِكَ
خدايا درهاى رحمتت را به روى ما بگشا،
وَانْشُرْ عَلَيْنا خَزائِنَ عُلُومِكَ بِرَحْمَتِكَ يا اَرْحَمَ الرّاحِمينَ
و خزانههاى علومت را بر ما باز كن به امید رحمتت اى مهربانترين مهربانان.
کتاب «فیزیولوژی پزشکی گایتون وهال» بهعنوان یکی از جامعترین و معتبرترین منابع در حوزه علوم پزشکی، همچنان مرجع کلیدی برای درک عملکرد پیچیده بدن انسان است. این اثر با تکیه بر تازهترین پژوهشها و توضیحات دقیق از سازوکارهای فیزیولوژیک، پلی میان علوم پایه پزشکی و کاربردهای بالینی ایجاد میکند و نقشی بیبدیل در آموزش، پژوهش و ارتقای دانش سلامت ایفا مینماید.
ترجمه دقیق و علمیاین شاهکار توسط برند علمیآیندهنگاران مغز به مدیریت داریوش طاهری، دسترسی فارسیزبانان به مرزهای نوین دانش فیزیولوژی را ممکن ساخته و رسالتی علمیبرای ارتقای آموزش پزشکی، فهم عمیقتر سازوکارهای بدن و توسعه روشهای نوین در حوزه سلامت فراهم آورده است.
» کتاب فیزیولوژی پزشکی گایتون وهال
» » فصل ۴۴: فیزیولوژی هوانوردی، نواحی مرتفع و فضانوردی
در حال ویرایش
» Guyton and Hall Textbook of Medical Physiology
»» CHAPTER 44: Aviation, High Altitude, and Space Physiology

As humans have ascended to higher and higher altitudes in aviation, mountain climbing, and space exploration, it has become progressively more important to understand the effects of altitude and low gas pressures on the human body. This chapter deals with these problems and acceleratory forces, weightlessness, and other challenges to body homeostasis that occur at high altitudes and in space flight.
همانطور که انسان در هوانوردی، کوه نوردی و اکتشافات فضایی به ارتفاعات بالاتر و بالاتر صعود کرده است، درک اثرات ارتفاع و فشار کم گاز بر بدن انسان به تدریج اهمیت بیشتری پیدا کرده است. این فصل به این مشکلات و نیروهای شتاب دهنده، بی وزنی و سایر چالشهای هموستاز بدن میپردازد که در ارتفاعات بالا و در پرواز فضایی رخ میدهد.
EFFECTS OF LOW OXYGEN PRESSURE ON THE BODY
Barometric Pressures at Different Altitudes. Table 44-1 lists the approximate barometric and oxygen pressures at different altitudes, showing that at sea level, the barometric pressure is 760 mm Hg; at 10,000 feet, it is only 523 mm Hg; and at 50,000 feet, it is 87 mm Hg. This decrease in barometric pressure is the basic cause of all the hypoxia problems in high-altitude physiology, because as the barometric pressure decreases, the atmospheric oxygen partial pressure (Po2) decreases proportionately, remaining at all times slightly less than 21% of the total barometric pressure; at sea level, Po2 is about 159 mm Hg, but at 50,000 feet, Po2 is only 18 mm Hg.
اثرات فشار کم اکسیژن بر روی بدن
فشارهای بارومتریک در ارتفاعات مختلف. جدول 1-44 فشارهای فشاری تقریبی و اکسیژن را در ارتفاعات مختلف فهرست میکند و نشان میدهد که در سطح دریا فشار هوا 760 میلیمتر جیوه است. در 10000 پا، تنها 523 میلی متر جیوه است. و در 50000 پا 87 میلی متر جیوه است. این کاهش فشار هوا دلیل اصلی همه مشکلات هیپوکسی در فیزیولوژی ارتفاعات است، زیرا با کاهش فشار هوا، فشار جزئی اکسیژن اتمسفر (Po2) به طور متناسب کاهش مییابد و در همه زمانها کمیکمتر از 21 درصد فشار بارومتری کل باقی میماند. در سطح دریا، Po2 حدود 159 میلی متر جیوه است، اما در 50000 فوت، Po2 تنها 18 میلی متر جیوه است.
ALVEOLAR PO2 AT DIFFERENT ELEVATIONS
Carbon Dioxide and Water Vapor Decrease the Alveolar Oxygen. Even at high altitudes, carbon dioxide (CO2) is continually excreted from the pulmonary blood into the alveoli. In addition, water vaporizes into the inspired air from the respiratory surfaces. These two gases dilute the O2 in the alveoli, thus reducing the O2 concentration. Water vapor pressure in the alveoli remains at 47 mm Hg as long as the body temperature is normal, regardless of altitude.
آلوئولار PO2 در ارتفاعات مختلف
دی اکسید کربن و بخار آب باعث کاهش اکسیژن آلوئولار میشود. حتی در ارتفاعات بالا، دی اکسید کربن (CO2) به طور مداوم از خون ریوی به آلوئولها دفع میشود. علاوه بر این، آب از سطوح تنفسی به هوای دمیده شده تبخیر میشود. این دو گاز O2 را در آلوئولها رقیق میکنند و در نتیجه غلظت O2 را کاهش میدهند. فشار بخار آب در آلوئولها تا زمانی که دمای بدن نرمال است، بدون توجه به ارتفاع، روی 47 میلی متر جیوه باقی میماند.
In the case of CO2, during exposure to very high altitudes, the alveolar partial pressure of CO2 (Pco2) falls from the sea level value of 40 mm Hg to lower values. In the acclimatized person, who increases ventilation about fivefold, the Pco, falls to about 7 mm Hg because of increased respiration.
در مورد CO2، در هنگام قرار گرفتن در معرض ارتفاعات بسیار بالا، فشار جزئی آلوئولی CO2 (Pco2) از مقدار سطح دریا 40 میلیمتر جیوه به مقادیر پایینتر کاهش مییابد. در فرد سازگار، که تهویه را حدود پنج برابر افزایش میدهد، Pco به دلیل افزایش تنفس به حدود 7 میلی متر جیوه میرسد.
Now let us see how the pressures of these two gases affect the alveolar O2. For example, assume that the barometric pressure falls from the normal sea level value of 760 to 253 mm Hg, which is the usual measured value at the top of 29,028-foot Mount Everest. Of this, 47 mm Hg must be water vapor, leaving only 206 mm Hg for all the other gases. In the acclimatized person, 7 mm Hg of the 206 mm Hg must be CO2, leaving only 199 mm Hg. If there were no use of O2 by the body, one-fifth of this 199 mm Hg would be O2 and four-fifths would be nitro- gen—that is, the Po2 in the alveoli would be 40 mm Hg. However, some of this remaining alveolar O2 is continually being absorbed into the blood, leaving about 35 mm Hg O2 pressure in the alveoli. At the summit of Mount Everest, only the best acclimatized people can barely survive when breathing air. However, the effect is very different when the person is breathing pure O2, as we see in the following discussions.
حال بیایید ببینیم که فشار این دو گاز چگونه بر O2 آلوئولی تأثیر میگذارد. به عنوان مثال، فرض کنید فشار هوا از مقدار نرمال سطح دریا 760 تا 253 میلیمتر جیوه کاهش مییابد، که مقدار معمول اندازهگیری شده در بالای قله 29028 فوتی اورست است. از این مقدار، 47 میلی متر جیوه باید بخار آب باشد و تنها 206 میلی متر جیوه برای همه گازهای دیگر باقی میماند. در فرد سازگار، 7 میلی متر جیوه از 206 میلی متر جیوه باید CO2 باشد و تنها 199 میلی متر جیوه باقی میماند. اگر بدن از O2 استفاده نمیکرد، یک پنجم این 199 میلی متر جیوه O2 و چهار پنجم آن نیتروژن خواهد بود، یعنی Po2 در آلوئولها 40 میلی متر جیوه خواهد بود. با این حال، مقداری از این O2 آلوئولی باقیمانده به طور مداوم در خون جذب میشود و حدود 35 میلی متر جیوه فشار O2 را در آلوئولها باقی میگذارد. در قله کوه اورست، تنها بهترین افراد سازگار با هوا به سختی میتوانند زنده بمانند. با این حال، همانطور که در بحثهای زیر میبینیم، زمانی که فرد O2 خالص تنفس میکند، تأثیر بسیار متفاوت است.
Alveolar Po2 at Different Altitudes. The fifth column of Table 44-1 shows the approximate Po2 values in the alveoli at different altitudes when one is breathing air for both the unacclimatized and the acclimatized person. At sea level, the alveolar Po2 is 104 mm Hg. At 20,000 feet altitude, it falls to about 40 mm Hg in the unacclimatized person but only to 53 mm Hg in the acclimatized person. The reason for the difference between these two is that alveolar ventilation increases much more in the acclimatized person than in the unacclimatized person, as we discuss later.
آلوئولار Po2 در ارتفاعات مختلف. ستون پنجم جدول 44-1 مقادیر تقریبی Po2 را در آلوئولها در ارتفاعات مختلف نشان میدهد، زمانی که فرد در حال تنفس هوا برای هر دو فرد سازگار و سازگار نشده است. در سطح دریا، Po2 آلوئولی 104 میلی متر جیوه است. در ارتفاع 20000 فوتی، در افراد سازگار نشده به حدود 40 میلیمتر جیوه میرسد، اما در فرد سازگار شده فقط به 53 میلیمتر جیوه میرسد. دلیل تفاوت بین این دو این است که تهویه آلوئولی در افراد سازگار شده بسیار بیشتر از افراد سازگار نشده افزایش مییابد، همانطور که بعداً بحث خواهیم کرد.
Saturation of Hemoglobin With Oxygen at Different Altitudes. Figure 44-1 shows arterial blood O2 saturation at different altitudes while a person is breathing air and while breathing O2. Up to an altitude of about 10,000 feet, even when air is breathed, the arterial O2 saturation remains at least as high as 90%. Above 10,000 feet, the arterial O2 saturation falls rapidly, as shown by the blue curve of the figure, until it is slightly less than 70% at 20,000 feet and much less at still higher altitudes.
اشباع هموگلوبین با اکسیژن در ارتفاعات مختلف. شکل 44-1 اشباع O2 خون شریانی را در ارتفاعات مختلف در حالی که فرد در حال تنفس هوا و هنگام تنفس O2 است نشان میدهد. تا ارتفاع حدود 10000 پا، حتی زمانی که هوا تنفس میشود، اشباع O2 شریانی حداقل تا 90 درصد باقی میماند. در بالای 10000 فوت، اشباع O2 شریانی به سرعت کاهش مییابد، همانطور که در منحنی آبی شکل نشان داده شده است، تا زمانی که در ارتفاع 20،000 پا کمیکمتر از 70 درصد و در ارتفاعات هنوز بسیار کمتر است.
EFFECT OF BREATHING PURE OXYGEN ON ALVEOLAR PO2 AT DIFFERENT ALTITUDES
When a person breathes pure O2 instead of air, most of the space in the alveoli formerly occupied by nitrogen becomes occupied by O2. At 30,000 feet, an aviator could have an alveolar Po2 as high as 139 mm Hg instead of 18 mm Hg when breathing air (see Table 44-1).
Table 44-1 Effects of Acute Exposure to Low Atmospheric Pressures on Alveolar Gas Concentrations and Arterial Oxygen Saturationa
جدول 44-1 اثرات مواجهه حاد با فشارهای اتمسفر پایین بر غلظت گاز آلوئولی و اشباع اکسیژن شریانی

aNumbers in parentheses are acclimatized values.
aاعداد داخل پرانتز مقادیر سازگار هستند.
اثر تنفس اکسیژن خالص بر روی PO2 آلوئولی در ارتفاعات مختلف
وقتی فردی به جای هوا O2 خالص تنفس میکند، بیشتر فضای آلوئولها که قبلاً توسط نیتروژن اشغال شده بود توسط O2 اشغال میشود. در ارتفاع 30000 پا، یک هوانورد میتواند در هنگام تنفس هوا به جای 18 میلی متر جیوه، PO2 آلوئولی تا 139 میلی متر جیوه داشته باشد (جدول 44-1 را ببینید).
The red curve of Figure 44-1 shows arterial blood hemoglobin O2 saturation at different altitudes when a person is breathing pure O2. Note that the saturation remains above 90% until the aviator ascends to about 39,000 feet; then it falls rapidly to about 50% at about 47,000 feet.
منحنی قرمز شکل 44-1 اشباع هموگلوبین O2 خون شریانی را در ارتفاعات مختلف زمانی که فرد O2 خالص تنفس میکند نشان میدهد. توجه داشته باشید که اشباع بالای 90٪ باقی میماند تا زمانی که هوانورد به حدود 39000 فوت صعود کند. سپس در ارتفاع 47000 فوتی به سرعت به حدود 50 درصد سقوط میکند.

Figure 44-1. Effect of high altitude on arterial oxygen saturation when breathing air or pure oxygen.
شکل 44-1. تأثیر ارتفاع زیاد بر اشباع اکسیژن شریانی هنگام تنفس هوا یا اکسیژن خالص.
The “Ceiling” When Breathing Air and When Breathing Oxygen in an Unpressurized Airplane. When comparing the two arterial blood O2 saturation curves in Figure 44-1, one notes that an aviator breathing pure O2 in an unpressurized airplane can ascend to far higher altitudes than one breathing air. For example, the arterial saturation at 47,000 feet when one is breathing O2 is about 50% and is equivalent to the arterial O2 saturation at 23,000 feet when one is breathing air. In addition, because an unacclimatized person usually can remain conscious until the arterial O2 saturation falls to 50%, the ceiling for an aviator for short exposure times in an unpressurized airplane when breathing air is about 23,000 feet and, when breathing pure O2, is about 47,000 feet, provided that the equipment supplying the O2 operates perfectly.
“سقف” هنگام تنفس هوا و هنگام تنفس اکسیژن در هواپیمای بدون فشار. هنگام مقایسه دو منحنی اشباع O2 خون شریانی در شکل 44-1، توجه میشود که یک خلبان که O2 خالص را در یک هواپیمای بدون فشار تنفس میکند، میتواند به ارتفاعات بسیار بالاتری نسبت به یک هوای تنفسی صعود کند. به عنوان مثال، اشباع شریانی در 47000 فوت زمانی که فرد در حال تنفس O2 است حدود 50% است و معادل اشباع O2 شریانی در 23000 فوت زمانی است که فرد در حال تنفس هوا است. علاوه بر این، از آنجایی که معمولاً یک فرد سازگار نشده میتواند تا زمانی که اشباع O2 شریانی به 50 درصد کاهش یابد، هوشیار بماند، سقف یک هوانورد برای زمانهای قرار گرفتن در معرض کوتاه در یک هواپیمای بدون فشار در هنگام تنفس هوا حدود 23000 فوت است و در هنگام تنفس O2 خالص حدود 47000 فوت است، مشروط بر اینکه تجهیزات O2 به طور کامل کار کنند.
ACUTE EFFECTS OF HYPOXIA
Some of the important acute effects of hypoxia in the unacclimatized person breathing air, beginning at an altitude of about 12,000 feet, are drowsiness, lassitude, mental and muscle fatigue, sometimes headache, occasionally nausea, and sometimes euphoria. These effects progress to a stage of twitchings or seizures above 18,000 feet and, above 23,000 feet in the unacclimatized person, end in coma, followed shortly thereafter by death.
اثرات حاد هیپوکسی
برخی از اثرات حاد مهم هیپوکسی در افراد غیرمجاز که از ارتفاع حدود 12000 پا شروع میشود، خواب آلودگی، بی حالی، خستگی ذهنی و عضلانی، گاهی سردرد، گاهی حالت تهوع و گاهی سرخوشی است. این اثرات به مرحله ای از انقباضات یا تشنجهای بالای 18000 فوت و در بالای 23000 فوت در فرد سازگار نشده، به کما ختم میشود و مدت کوتاهی پس از آن با مرگ همراه میشود.
One of the most important effects of hypoxia is decreased mental proficiency, which decreases judgment, memory, and performance of discrete motor movements. For example, if an unacclimatized aviator stays at 15,000 feet for 1 hour, mental proficiency ordinarily falls to about 50% of normal and, after 18 hours at this level, it falls to about 20% of normal.
یکی از مهم ترین اثرات هیپوکسی کاهش مهارت ذهنی است که باعث کاهش قضاوت، حافظه و عملکرد حرکات حرکتی گسسته میشود. برای مثال، اگر یک خلبان هوانوردی که هوانوردی ندارد به مدت 1 ساعت در ارتفاع 15000 پا بماند، مهارت ذهنی معمولاً به حدود 50 درصد نرمال میرسد و پس از 18 ساعت در این سطح، به حدود 20 درصد عادی میرسد.
ACCLIMATIZATION TO LOW Po2
A person remaining at high altitudes for days, weeks, or years becomes more and more acclimatized to the low Po2, so it causes fewer deleterious effects on the body. After acclimatization, it becomes possible for the person to work harder without hypoxic effects or to ascend to still higher altitudes.
سازگاری با Po2 کم
فردی که برای روزها، هفتهها یا سالها در ارتفاعات باقی میماند، بیشتر و بیشتر با Po2 کم سازگار میشود، بنابراین اثرات مضر کمتری بر بدن ایجاد میکند. پس از سازگاری، این امکان برای فرد ایجاد میشود که بدون اثرات هیپوکسیک بیشتر کار کند یا به ارتفاعات هنوز بالاتر صعود کند.
The principal means whereby acclimatization comes about are as follows: (1) a great increase in pulmonary ventilation; (2) increased numbers of red blood cells; (3) increased diffusing capacity of the lungs; (4) increased vascularity of the peripheral tissues; and (5) increased ability of the tissue cells to use O2, despite low Po2.
ابزار اصلی که از طریق آن سازگاری انجام میشود به شرح زیر است: (1) افزایش زیاد در تهویه ریوی. (2) افزایش تعداد گلبولهای قرمز. (3) افزایش ظرفیت انتشار ریهها. (4) افزایش عروق بافتهای محیطی. و (5) افزایش توانایی سلولهای بافت برای استفاده از O2، با وجود Po2 کم.
Increased Pulmonary Ventilation-Role of Arterial Chemoreceptors. Immediate exposure to low Po2 stimulates the arterial chemoreceptors, and this stimulation increases alveolar ventilation to a maximum of about 1.65 times normal. Therefore, compensation occurs within seconds for the high altitude, and this alone allows the person to rise several thousand feet higher than would be possible without the increased ventilation. If the person remains at a very high altitude for several days, the chemoreceptors increase ventilation still more, up to about five times normal.
افزایش تهویه ریوی – نقش گیرندههای شیمیایی شریانی. قرار گرفتن فوری در معرض Po2 کم، گیرندههای شیمیایی شریانی را تحریک میکند و این تحریک تهویه آلوئولی را حداکثر تا حدود 1.65 برابر طبیعی افزایش میدهد. بنابراین، جبران در عرض چند ثانیه برای ارتفاع زیاد اتفاق میافتد و این به تنهایی به فرد اجازه میدهد تا چندین هزار فوت بالاتر از آن چیزی که بدون افزایش تهویه ممکن است، برود. اگر فرد چندین روز در ارتفاع بسیار بالا بماند، گیرندههای شیمیایی تهویه را بیشتر افزایش میدهند، تا حدود پنج برابر نرمال.
The immediate increase in pulmonary ventilation on rising to a high altitude blows off large quantities of CO2, reducing the Pco, and increasing the pH of the body fluids. These changes inhibit the brain stem respiratory center and thereby oppose the effect of low Po2 tostimu late respiration via the peripheral arterial chemoreceptors in the carotid and aortic bodies. However, this inhibition fades away during the ensuing 2 to 5 days, allowing the respiratory center to respond with full force to the peripheral chemoreceptor stimulus from hypoxia, and ventilation increases to about five times normal.
افزایش فوری تهویه ریوی هنگام صعود به ارتفاعات، مقادیر زیادی CO2 را دفع میکند، Pco را کاهش میدهد و pH مایعات بدن را افزایش میدهد. این تغییرات مرکز تنفسی ساقه مغز را مهار میکند و در نتیجه با اثر تنفس دیرهنگام کم Po2 از طریق گیرندههای شیمیایی شریانی محیطی در بدن کاروتید و آئورت مخالفت میکند. با این حال، این مهار در طی 2 تا 5 روز بعد از بین میرود و به مرکز تنفسی اجازه میدهد با نیروی کامل به محرک گیرنده شیمیایی محیطی ناشی از هیپوکسی پاسخ دهد و تهویه تا حدود پنج برابر نرمال افزایش مییابد.
The cause of this fading inhibition is believed to be mainly a reduction of bicarbonate ion concentration in the cerebrospinal fluid, as well as in the brain tissues. This reduction, in turn, decreases the pH in the fluids sur- rounding the chemosensitive neurons of the respiratory center, thus increasing the respiratory stimulatory activity of the center.
اعتقاد بر این است که علت این مهار محو شدن عمدتاً کاهش غلظت یون بی کربنات در مایع مغزی نخاعی و همچنین در بافتهای مغز است. این کاهش، به نوبه خود، pH مایعات اطراف نورونهای شیمیایی حساس مرکز تنفسی را کاهش میدهد و در نتیجه فعالیت تحریکی تنفسی مرکز را افزایش میدهد.
An important mechanism for the gradual decrease in bicarbonate concentration is compensation by the kidneys for the respiratory alkalosis, as discussed in Chapter 31. The kidneys respond to decreased Pco, by reducing hydrogen ion secretion and increasing bicarbonate excretion. This metabolic compensation for the respiratory alkalosis gradually reduces plasma and cerebrospinal fluid bicarbonate concentrations and pH toward normal and removes part of the inhibitory effect on respiration of a low hydrogen ion concentration. Thus, the respiratory centers are much more responsive to the peripheral chemoreceptor stimulus caused by the hypoxia after the kidneys compensate for the alkalosis.
یک مکانیسم مهم برای کاهش تدریجی غلظت بی کربنات، جبران آلکالوز تنفسی توسط کلیهها است، همانطور که در فصل 31 بحث شد. کلیهها با کاهش ترشح یون هیدروژن و افزایش دفع بی کربنات به کاهش Pco پاسخ میدهند. این جبران متابولیکی برای آلکالوز تنفسی به تدریج غلظت بی کربنات پلاسما و مایع مغزی نخاعی و pH را به سمت نرمال کاهش میدهد و بخشی از اثر بازدارنده در تنفس غلظت یون هیدروژن پایین را حذف میکند. بنابراین، مراکز تنفسی پس از جبران آلکالوز توسط کلیهها، بسیار بیشتر به محرکهای گیرنده شیمیایی محیطی ناشی از هیپوکسی پاسخ میدهند.
Increase in Red Blood Cells and Hemoglobin Concentration During Acclimatization. As discussed in Chapter 33, hypoxia is a major stimulus for increasing red blood cell production. Ordinarily, when a person remains exposed to low O2 for weeks at a time, the hematocrit rises slowly from a normal value of 40% to 45% to an aver- age of about 60%, with an average increase in whole blood hemoglobin concentration from a normal value of 15 g/dl to about 20 g/dl.
افزایش گلبولهای قرمز خون و غلظت هموگلوبین در طول سازگاری. همانطور که در فصل 33 بحث شد، هیپوکسی یک محرک اصلی برای افزایش تولید گلبولهای قرمز است. به طور معمول، زمانی که فرد برای هفتهها در معرض اکسیژن کم قرار میگیرد، هماتوکریت به آرامیاز مقدار نرمال 40% به 45% به میانگین 60% افزایش مییابد، با میانگین افزایش غلظت هموگلوبین کل خون از مقدار طبیعی 15 گرم در دسی لیتر به حدود 20 گرم در دسی لیتر.
In addition, the blood volume also increases, often by 20% to 30%, and this increase, multiplied by the increased blood hemoglobin concentration, gives an increase in total body hemoglobin of 50% or more.
علاوه بر این، حجم خون نیز اغلب بین 20 تا 30 درصد افزایش مییابد و این افزایش، ضرب در افزایش غلظت هموگلوبین خون، باعث افزایش هموگلوبین کل بدن 50 درصد یا بیشتر میشود.
Increased Diffusing Capacity After Acclimatization. The normal diffusing capacity for O2 through the pulmonary membrane is about 21 ml/mm Hg per minute, and this diffusing capacity can increase as much as 3-fold during exercise. A similar increase in diffusing capacity occurs at high altitudes.
افزایش ظرفیت انتشار پس از سازگاری. ظرفیت انتشار طبیعی O2 از طریق غشای ریوی حدود 21 میلیلیتر بر میلیمتر جیوه در دقیقه است و این ظرفیت انتشار میتواند در طول ورزش تا 3 برابر افزایش یابد. افزایش مشابهی در ظرفیت انتشار در ارتفاعات بالا رخ میدهد.
Part of the increase results from increased pulmonary capillary blood volume, which expands the capillaries and increases the surface area through which O2 can diffuse into the blood. Another part of this increase results from an increase in lung air volume, which expands the surface area of the alveolar-capillary interface still more. A final part results from an increase in pulmonary arterial blood pressure, which forces blood into greater numbers of alveolar capillaries than normal, especially in the upper parts of the lungs, which are poorly perfused under usual conditions.
بخشی از این افزایش ناشی از افزایش حجم خون مویرگی ریوی است که مویرگها را گسترش میدهد و سطحی را افزایش میدهد که از طریق آن O2 میتواند در خون منتشر شود. بخش دیگری از این افزایش ناشی از افزایش حجم هوای ریه است که سطح سطح رابط آلوئولی-مویرگی را بیشتر گسترش میدهد. بخش نهایی ناشی از افزایش فشار خون شریانی ریوی است که خون را به تعداد بیشتری از مویرگهای آلوئولی نسبت به حالت عادی وادار میکند، به خصوص در قسمتهای بالایی ریهها، که در شرایط معمول به خوبی پرفیوژن میشوند.
Peripheral Circulatory System Changes During Acclimatization-Increased Tissue Capillarity. The cardiac output often increases as much as 30% immediately after a person ascends to a high altitude but then decreases back toward normal over a period of weeks as the blood hematocrit increases, so the amount of O2 transported to the peripheral body tissues remains about normal.
تغییرات سیستم گردش خون محیطی در طول سازگاری – افزایش مویرگ بافتی. برون ده قلبی اغلب بلافاصله پس از صعود فرد به ارتفاع بالا تا 30 درصد افزایش مییابد، اما پس از چند هفته با افزایش هماتوکریت خون به حالت عادی کاهش مییابد، بنابراین مقدار O2 منتقل شده به بافتهای محیطی بدن تقریباً نرمال باقی میماند.
Another circulatory adaptation is growth of increased numbers of systemic circulatory capillaries in the non- pulmonary tissues, called angiogenesis. This adaptation occurs especially in animals born and bred at high alti- tudes but less so in animals that become exposed to high altitudes later in life.
یکی دیگر از سازگاریهای گردش خون، رشد افزایش تعداد مویرگهای گردش خون سیستمیک در بافتهای غیر ریوی است که به آن رگ زایی میگویند. این سازگاری به ویژه در حیواناتی که در ارتفاعات به دنیا میآیند و پرورش یافتهاند، اتفاق میافتد، اما در حیواناتی که بعداً در معرض ارتفاعات قرار میگیرند، کمتر اتفاق میافتد.
In active tissues exposed to chronic hypoxia, the increase in capillarity is especially marked. For example, capillary density in right ventricular muscle increases markedly because of the combined effects of hypoxia and excess workload on the right ventricle caused by pulmonary hypertension at high altitude.
در بافتهای فعالی که در معرض هیپوکسی مزمن قرار دارند، افزایش مویرگ به ویژه مشخص میشود. به عنوان مثال، تراکم مویرگی در عضله بطن راست به طور قابل توجهی به دلیل اثرات ترکیبی هیپوکسی و بار کاری بیش از حد بر روی بطن راست ناشی از فشار خون ریوی در ارتفاع بالا افزایش مییابد.
Cellular Acclimatization. In animals native to altitudes of 13,000 to 17,000 feet, cell mitochondria and cellular oxidative enzyme systems are slightly more plentiful than in sea level inhabitants. Therefore, it is presumed that the tissue cells of high altitude-acclimatized human beings also can use O2 more effectively than can their sea level counterparts.
سازگاری سلولی .در حیوانات بومیارتفاعات 13000 تا 17000 پا، میتوکندری سلولی و سیستم آنزیم اکسیداتیو سلولی کمیبیشتر از ساکنان سطح دریا است. بنابراین، فرض بر این است که سلولهای بافتی انسانهایی که در ارتفاع بالا همخونی شدهاند نیز میتوانند از O2 به طور مؤثرتری نسبت به همتایان خود در سطح دریا استفاده کنند.
HYPOXIA-INDUCIBLE FACTORS-A “MASTER SWITCH” FOR THE BODY’S RESPONSE TO HYPOXIA
Hypoxia-inducible factors (HIFs) are DNA-binding transcription factors that respond to decreased oxygen availability and activate several genes that encode proteins needed for adequate oxygen delivery to tissues and energy metabolism. HIFs are found in virtually all oxygen- breathing species, ranging from primitive worms to humans. Some of the genes controlled by HIFs, especially HIF-1, include the following:
هیپوکسی-عوامل القایی-یک “سوئیچ اصلی” برای پاسخ بدن به هیپوکسی
عوامل القا کننده هیپوکسی (HIFs) فاکتورهای رونویسی متصل شونده به DNA هستند که به کاهش در دسترس بودن اکسیژن پاسخ میدهند و چندین ژن را فعال میکنند که پروتئینهای مورد نیاز برای رساندن اکسیژن کافی به بافتها و متابولیسم انرژی را کد میکنند. HIFها تقریباً در همه گونههای تنفسی با اکسیژن یافت میشوند، از کرمهای اولیه گرفته تا انسان. برخی از ژنهای کنترل شده توسط HIF، به ویژه HIF-1، شامل موارد زیر است:
• Genes associated with vascular endothelial growth factor, which stimulates angiogenesis
• Erythropoietin genes that stimulate red blood cell production
• Mitochondrial genes involved with energy utilization
• Glycolytic enzyme genes involved with anaerobic metabolism
• Genes that increase availability of nitric oxide, which causes pulmonary vasodilation
• ژنهای مرتبط با فاکتور رشد اندوتلیال عروقی، که رگزایی را تحریک میکند
• ژنهای اریتروپویتین که تولید گلبولهای قرمز را تحریک میکنند
• ژنهای میتوکندریایی دخیل در مصرف انرژی
• ژنهای آنزیم گلیکولیتیک دخیل در متابولیسم بیهوازی
• ژنهایی که در دسترس بودن اکسید نیتریک را افزایش میدهند، که باعث گشاد شدن عروق ریوی میشود
In the presence of adequate oxygen, the subunits of HIF required to activate various genes are downregulated and inactivated by specific HIF hydroxylases. In hypoxia, the HIF hydroxylases are themselves inactive, allowing the formation of a transcriptionally active HIF complex. Thus, the HIFs serve as a “master switch” that permits the body to respond appropriately to hypoxia.
در حضور اکسیژن کافی، زیرواحدهای HIF مورد نیاز برای فعال کردن ژنهای مختلف توسط هیدروکسیلازهای خاص HIF تنظیم و غیرفعال میشوند. در هیپوکسی، هیدروکسیلازهای HIF خود غیر فعال هستند و امکان تشکیل یک کمپلکس HIF فعال رونویسی را فراهم میکنند. بنابراین، HIFها به عنوان یک “سوئیچ اصلی” عمل میکنند که به بدن اجازه میدهد به طور مناسب به هیپوکسی پاسخ دهد.
NATURAL ACCLIMATIZATION OF NATIVE PEOPLE LIVING AT HIGH ALTITUDES
Many native people in the Andes and in the Himalayas live at altitudes above 13,000 feet. One group in the Peruvian Andes lives at an altitude of 17,500 feet and works in a mine at an altitude of 19,000 feet. Many of these natives are born at these high altitudes and live there all their lives. They are superior to even the best-acclimatized lowlanders in all aspects of acclimatization, even though the lowlanders might have lived at high altitudes for 10 or more years. Acclimatization of the natives begins in infancy. The chest size, especially, is greatly increased, whereas the body size is somewhat decreased, giving a high ratio of ventilatory capacity to body mass. The hearts of natives, which from birth onward pump extra amounts of cardiac output, are also considerably larger than the hearts of lowlanders.
سازگاری طبیعی افراد بومیساکن در ارتفاعات
بسیاری از مردم بومیآند و هیمالیا در ارتفاعات بالای 13000 پا زندگی میکنند. یک گروه در آند پرو در ارتفاع 17500 فوتی زندگی میکنند و در معدنی در ارتفاع 19000 فوتی کار میکنند. بسیاری از این بومیان در این ارتفاعات به دنیا میآیند و تمام عمر خود را در آنجا زندگی میکنند. آنها حتی در تمام جنبههای سازگاری حتی از مناطق پست که به بهترین وجه سازگار شده اند، برتر هستند، حتی اگر زمینهای پست ممکن است 10 سال یا بیشتر در ارتفاعات بالا زندگی کرده باشند. سازگاری بومیان از دوران نوزادی آغاز میشود. اندازه قفسه سینه، به ویژه، بسیار افزایش مییابد، در حالی که اندازه بدن تا حدودی کاهش مییابد، و نسبت بالایی از ظرفیت تهویه به توده بدن را میدهد. قلب بومیان که از بدو تولد به بعد برون ده قلبی بیشتری را پمپاژ میکنند نیز به طور قابل توجهی بزرگتر از قلب مردم پست است.
Delivery of O2 by the blood to the tissues is also highly facilitated in these natives. For example, Figure 44-2 shows O2-hemoglobin dissociation curves for natives who live at sea level and for their counterparts who live at 15,000 feet. Note that the arterial Po2 in the natives at a high altitude is only 40 mm Hg but, because of the greater quantity of hemoglobin, the quantity of O2 in their arterial blood is greater than that in the blood of the natives at the lower altitude. Note also that the venous Po2 in the high-altitude natives is only 15 mm Hg less than the venous Po, for the lowlanders, despite the very low arterial Po2, indicating that O2 transport to the tissues is exceedingly effective in the naturally acclimatized high-altitude natives.
تحویل O2 توسط خون به بافتها نیز در این افراد بومیبسیار تسهیل میشود. به عنوان مثال، شکل 44-2 منحنیهای تفکیک هموگلوبین O2 را برای بومیان ساکن در سطح دریا و برای همتایان آنها که در ارتفاع 15000 فوتی زندگی میکنند نشان میدهد. توجه داشته باشید که Po2 شریانی در بومیان در ارتفاع بالا تنها 40 میلی متر جیوه است، اما به دلیل مقدار بیشتر هموگلوبین، مقدار O2 در خون شریانی آنها بیشتر از خون بومیان در ارتفاع پایین تر است. همچنین توجه داشته باشید که Po2 وریدی در بومیان ارتفاع بالا تنها 15 میلیمتر جیوه کمتر از Po وریدی است، برای ساکنان پست، علیرغم Po2 شریانی بسیار کم، که نشان میدهد انتقال O2 به بافتها در بومیان ارتفاع بالا که به طور طبیعی سازگار شدهاند، بسیار مؤثر است.
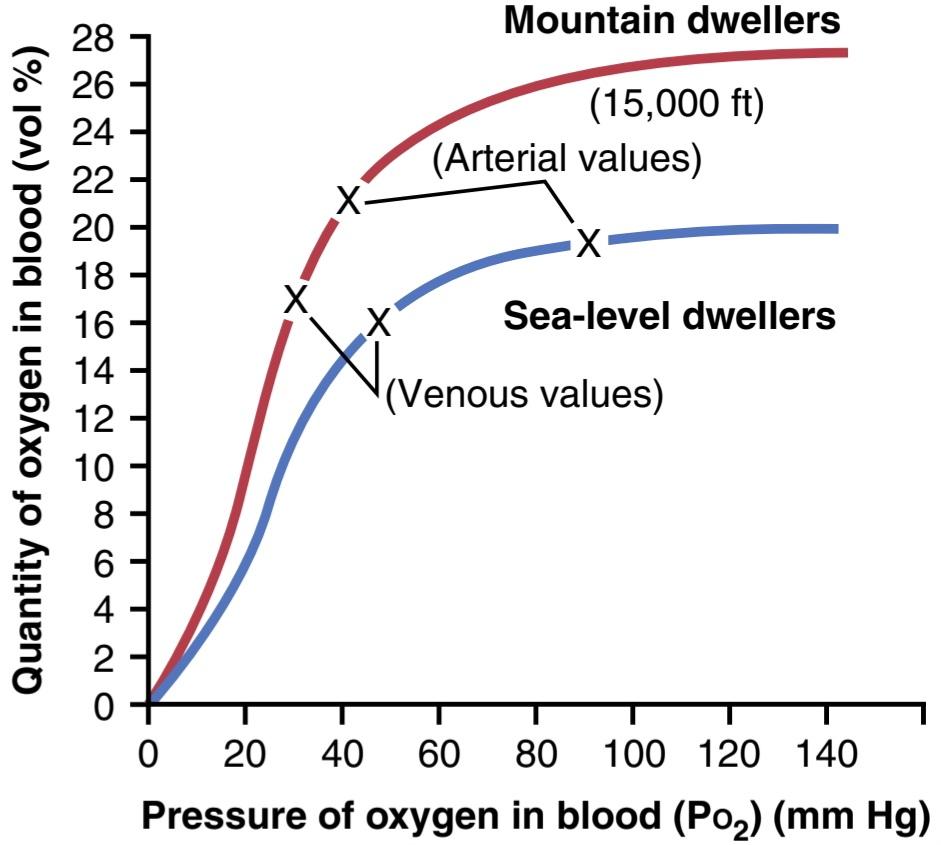
Figure 44-2. Oxygen-hemoglobin dissociation curves for blood of high-altitude residents (red curve) and sea level residents (blue curve) showing the respective arterial and venous Po2 levels and oxygen contents as recorded in their native surroundings. (Data from Pan American Health Organization. Oxygen-dissociation curves for bloods of high-altitude and sea-level residents. Life at high altitudes. Washington, DC: Pan American Health Organization Scientific Publication No. 140, 1966.)
شکل 44-2. منحنیهای تفکیک اکسیژن-هموگلوبین برای خون ساکنان ارتفاع بالا (منحنی قرمز) و ساکنان سطح دریا (منحنی آبی) که سطوح Po2 شریانی و وریدی مربوطه و محتوای اکسیژن را که در محیط بومیآنها ثبت شده است نشان میدهد. (دادههای سازمان بهداشت پان آمریکا. منحنیهای تفکیک اکسیژن برای خون ساکنان ارتفاعات و سطح دریا. زندگی در ارتفاعات بالا. واشنگتن دی سی: انتشارات علمیسازمان بهداشت پان آمریکا شماره 140، 1966.)
REDUCED WORK CAPACITY AT HIGH ALTITUDES AND POSITIVE EFFECT OF ACCLIMATIZATION
In addition to the mental depression caused by hypoxia, the work capacity of all muscles, cardiac as well as skeletal muscle, is greatly decreased in a state of hypoxia. In general, work capacity is reduced in direct proportion to the decrease in maximum rate of O2 uptake that the body can achieve.
کاهش ظرفیت کاری در ارتفاعات بالا و اثر مثبت سازگاری
علاوه بر افسردگی روانی ناشی از هیپوکسی، ظرفیت کار همه عضلات، قلبی و اسکلتی، در حالت هیپوکسی به شدت کاهش مییابد. به طور کلی، ظرفیت کار به نسبت مستقیم با کاهش حداکثر سرعت جذب O2 که بدن میتواند به دست آورد، کاهش مییابد.
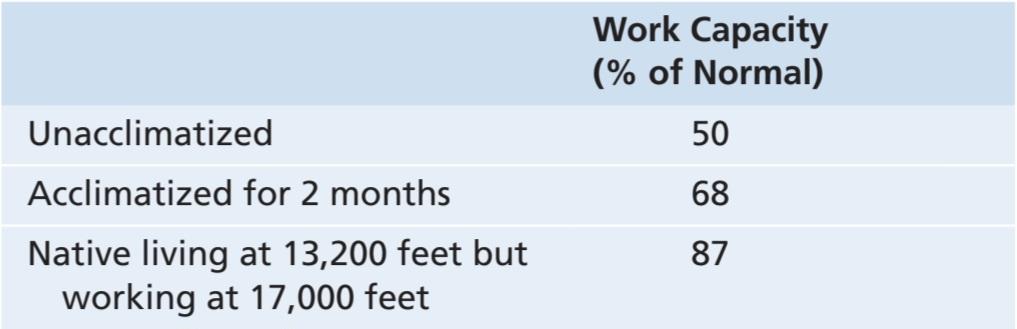
To give an idea of the importance of acclimatization in increasing work capacity, consider the large differences in work capacities as a percentage of normal for unacclimatized and acclimatized people at an altitude of 17,000 feet, shown in Table 44-2. Thus, naturally acclimatized native persons can achieve a daily work output even at a high altitude almost equal to that of a lowlander at sea level, but even well-acclimatized lowlanders can almost never achieve this result.
برای درک اهمیت سازگاری در افزایش ظرفیت کاری، تفاوتهای بزرگ در ظرفیتهای کاری را به عنوان درصدی از نرمال برای افراد ناهمخوان و سازگار در ارتفاع 17000 فوتی در نظر بگیرید که در جدول 44-2 نشان داده شده است. بنابراین، افراد بومیبه طور طبیعی میتوانند بازده کار روزانه را حتی در ارتفاعات بالا تقریباً برابر با یک زمین پست در سطح دریا به دست آورند، اما حتی مناطق پست که به خوبی هم هوا شده اند تقریباً هرگز نمیتوانند به این نتیجه دست یابند.
Table 44-2 Differences in Work Capacities
جدول ۴۴-۲ تفاوتها در ظرفیتهای کاری
ACUTE MOUNTAIN SICKNESS AND HIGH- ALTITUDE PULMONARY EDEMA
A small percentage of people who ascend rapidly to high altitudes become acutely sick and can die if not given O2 or rapidly moved to a low altitude. The sickness begins from a few hours up to about 2 days after ascent. Two events frequently occur:
بیماری حاد کوهستانی و ادم ریوی در ارتفاع بالا
درصد کمیاز افرادی که به سرعت به ارتفاعات بالا میروند، در صورت عدم دریافت اکسیژن یا انتقال سریع به ارتفاع کم، به شدت بیمار میشوند و میتوانند بمیرند. بیماری از چند ساعت تا حدود 2 روز پس از صعود شروع میشود. دو رویداد اغلب رخ میدهد:
1. Acute cerebral edema. This edema is believed to result from local vasodilation of the cerebral blood vessels, which is caused by the hypoxia. Dilation of the arterioles increases blood flow into the capillaries, thus increasing capillary pressure, which in turn causes fluid to leak into the cerebral tissues. Chemical factors such as vascular endothelial growth factor and inflammatory cytokines may also contribute to edema by increasing endothelial cell permeability. The cerebral edema can then lead to severe disorientation and other effects related to cerebral dysfunction.
1. ادم حاد مغزی. اعتقاد بر این است که این ادم ناشی از اتساع موضعی عروق خونی مغز است که ناشی از هیپوکسی است. اتساع شریانها باعث افزایش جریان خون در مویرگها میشود و در نتیجه فشار مویرگها را افزایش میدهد که به نوبه خود باعث نشت مایع به بافتهای مغز میشود. عوامل شیمیایی مانند فاکتور رشد اندوتلیال عروقی و سایتوکاینهای التهابی نیز ممکن است با افزایش نفوذپذیری سلولهای اندوتلیال به ادم کمک کنند. سپس ادم مغزی میتواند منجر به بی نظمیشدید و سایر اثرات مربوط به اختلال عملکرد مغزی شود.
2. Acute pulmonary edema. The cause of acute pulmonary edema is still uncertain, but may be explained by the following. The severe hypoxia causes the pulmonary arterioles to constrict powerfully, but the constriction is much greater in some parts of the lungs than in other parts, so more and more of the pulmonary blood flow is forced through fewer and fewer still unconstricted pulmonary vessels. The postulated result is that the capillary pressure in these areas of the lungs becomes especially high, and local edema occurs. Extension of the process to progressively more areas of the lungs leads to spreading pulmonary edema and severe pulmonary dysfunction that can be lethal. Allowing the person to breathe O2 usually reverses the process within hours. The same chemical factors that have been suggested to increase capillary permeability in the brain may also contribute to increased pulmonary capillary permeability and edema in the lungs.
2. ادم حاد ریوی. علت ادم حاد ریوی هنوز نامشخص است، اما ممکن است با موارد زیر توضیح داده شود. هیپوکسی شدید باعث انقباض شدید شریانهای ریوی میشود، اما این انقباض در برخی از قسمتهای ریه بسیار بیشتر از سایر قسمتها است، بنابراین جریان خون ریوی بیشتر و بیشتر از طریق عروق ریوی کمتر و هنوز منقبض نشده است. نتیجه فرضی این است که فشار مویرگی در این نواحی از ریهها به ویژه بالا میرود و ادم موضعی رخ میدهد. گسترش روند به تدریج به مناطق بیشتری از ریهها منجر به گسترش ادم ریوی و اختلال شدید عملکرد ریوی میشود که میتواند کشنده باشد. اجازه دادن به فرد برای تنفس O2 معمولاً ظرف چند ساعت روند را معکوس میکند. همان عوامل شیمیایی که برای افزایش نفوذپذیری مویرگی در مغز پیشنهاد شدهاند، ممکن است به افزایش نفوذپذیری مویرگی ریوی و ادم در ریهها نیز کمک کنند.
CHRONIC MOUNTAIN SICKNESS
Occasionally, a person who remains at a high altitude too long experiences chronic mountain sickness, in which the following effects occur:
بیماری مزمن کوهستانی
گاهی اوقات، فردی که برای مدت طولانی در ارتفاعات باقی میماند، بیماری کوهستانی مزمن را تجربه میکند که در آن عوارض زیر رخ میدهد:
1. The red blood cell mass and hematocrit become exceptionally high.
2. The pulmonary arterial pressure becomes elevated even more than the normal elevation that occurs during acclimatization.
3. The right side of the heart becomes greatly enlarged.
4. The peripheral arterial pressure begins to fall.
5. Congestive heart failure ensues.
6. Death often follows unless the person is moved to a lower altitude.
1. توده گلبول قرمز و هماتوکریت فوق العاده بالا میرود.
2. فشار شریانی ریوی حتی بیشتر از افزایش طبیعی که در طول سازگاری رخ میدهد، افزایش مییابد.
3. سمت راست قلب به شدت بزرگ میشود.
4. فشار شریانی محیطی شروع به کاهش میکند.
5. نارسایی احتقانی قلب ایجاد میشود.
6. مرگ اغلب به دنبال دارد مگر اینکه فرد به ارتفاع پایینتری منتقل شود.
There are probably three main causes of this sequence of events:
احتمالاً سه دلیل اصلی برای این توالی وقایع وجود دارد:
1. The red blood cell mass becomes so great that the blood viscosity increases severalfold. This increased viscosity tends to decrease tissue blood flow so that O2 delivery also begins to decrease.
1. توده گلبول قرمز آنقدر زیاد میشود که ویسکوزیته خون چندین برابر میشود. این افزایش ویسکوزیته باعث کاهش جریان خون بافتی میشود به طوری که تحویل O2 نیز شروع به کاهش میکند.
2. The pulmonary arterioles become vasoconstricted because of the lung hypoxia. This vasoconstriction results from the hypoxic vascular constrictor effect that normally operates to divert blood flow from low-O2 to high-O2 alveoli, as explained in Chapter 39. However, because all the alveoli are now in the low-O2 state, all the arterioles become constricted, the pulmonary arterial pressure rises excessively, and the right side of the heart fails.
۲. شریانهای ریوی به دلیل هیپوکسی ریه دچار انقباض عروقی میشوند. این انقباض عروقی ناشی از اثر انقباض عروقی هیپوکسیک است که به طور معمول برای منحرف کردن جریان خون از آلوئولهای با O2 پایین به آلوئولهای با O2 بالا عمل میکند، همانطور که در فصل ۳۹ توضیح داده شده است. با این حال، از آنجا که اکنون تمام آلوئولها در حالت O2 پایین هستند، تمام شریانها منقبض میشوند، فشار شریان ریوی بیش از حد افزایش مییابد و سمت راست قلب از کار میافتد.
3. The alveolar arteriolar spasm diverts much of the blood flow through nonalveolar pulmonary vessels, thus causing an excess of pulmonary shunt blood flow where the blood is poorly oxygenated, which further compounds the problem. Most people with this condition recover within days or weeks when they are moved to a lower altitude.
۳. اسپاسم شریانچههای آلوئولی بخش زیادی از جریان خون را از طریق رگهای ریوی غیرآلوئولی منحرف میکند و در نتیجه باعث افزایش جریان خون شنت ریوی در جایی میشود که خون اکسیژن کمیدارد و این مشکل را پیچیدهتر میکند. اکثر افراد مبتلا به این بیماری در عرض چند روز یا چند هفته پس از انتقال به ارتفاع پایینتر بهبود مییابند.
Effects of Acceleratory Forces on the Body in Aviation and Space Physiology
Because of rapid changes in velocity and direction of motion in airplanes or spacecraft, several types of acceleratory forces affect the body during flight. At the beginning of flight, simple linear acceleration occurs, at the end of flight, deceleration occurs, and every time the vehicle turns, centrifugal acceleration occurs.
اثرات نیروهای شتاب دهنده بر بدن در فیزیولوژی هوانوردی و فضایی
به دلیل تغییرات سریع در سرعت و جهت حرکت در هواپیماها یا فضاپیماها، چندین نوع نیروی شتاب بر بدن در طول پرواز تأثیر میگذارد. در ابتدای پرواز، شتاب خطی ساده، در پایان پرواز، کاهش سرعت رخ میدهد و هر بار که وسیله نقلیه میچرخد، شتاب گریز از مرکز رخ میدهد.
Centrifugal Acceleratory Forces
When an airplane makes a turn, the force of centrifugal acceleration is determined by the following relationship:
نیروهای شتاب دهنده گریز از مرکز
هنگامیکه یک هواپیما میچرخد، نیروی شتاب گریز از مرکز با رابطه زیر تعیین میشود:

in which fis centrifugal acceleratory force, m is the mass of the object, v is velocity of travel, and r is the radius of curvature of the turn. From this formula, it is obvious that as the velocity increases, the force of centrifugal acceleration increases in proportion to the square of the velocity. It is also obvious that the force of acceleration is directly proportional to the sharpness of the turn (the less the radius).
که در آن نیروی شتاب گریز از مرکز fis، m جرم جسم، v سرعت حرکت، و r شعاع انحنای چرخش است. از این فرمول مشخص میشود که با افزایش سرعت، نیروی شتاب گریز از مرکز به نسبت مجذور سرعت افزایش مییابد. همچنین بدیهی است که نیروی شتاب با شدت پیچ (هرچه شعاع کمتر باشد) نسبت مستقیم دارد.
Measurement of Acceleratory Force “G.” When an aviator is simply sitting in his seat, the force with which he or she is pressing against the seat results from the pull of gravity and is equal to the person’s weight. The intensity of this force is said to be +1 G because it is equal to the pull of gravity. If the force with which the person presses against the seat becomes five times the normal weight during pull-out from a dive, the force acting on the seat is +5 G.
اندازه گیری نیروی شتاب “G.” هنگامیکه یک هوانورد به سادگی روی صندلی خود مینشیند، نیرویی که با آن به صندلی فشار میآورد ناشی از کشش گرانش است و با وزن فرد برابر است. شدت این نیرو را 1+ G میگویند زیرا برابر با کشش گرانش است. اگر نیرویی که فرد به صندلی فشار میآورد در هنگام بیرون کشیدن از شیرجه پنج برابر وزن معمولی شود، نیروی وارد بر صندلی +5 گرم است.
If the airplane goes through an outside loop so that the person is held down by the seat belt, negative G is applied to the body. If the force with which the person is held down by the seat belt is equal to the weight of the body, the negative force is -1 G.
اگر هواپیما از یک حلقه بیرونی عبور کند به طوری که فرد توسط کمربند ایمنی نگه داشته شود، G منفی به بدن اعمال میشود. اگر نیرویی که فرد با آن توسط کمربند ایمنی نگه داشته میشود برابر با وزن بدن باشد، نیروی منفی 1- گرم است.
Effects of Centrifugal Acceleratory Force on the Body (Positive G)
Effects on the Circulatory System. The most important effect of centrifugal acceleration is on the circulatory system because blood is mobile and can be translocated by centrifugal forces.
اثرات نیروی شتاب گریز از مرکز بر بدن (G مثبت)
اثرات بر سیستم گردش خون. مهمترین اثر شتاب گریز از مرکز بر سیستم گردش خون است زیرا خون متحرک است و توسط نیروهای گریز از مرکز قابل جابجایی است.
When an aviator is subjected to positive G, blood is centrifuged toward the lowermost part of the body. Thus, if the centrifugal acceleratory force is +5 G and the person is in an immobilized standing position, the pressure in the veins of the feet becomes greatly increased (to ≈450 mm Hg). In the sitting position, the pressure becomes nearly 300 mm Hg. In addition, as pressure in the vessels of the lower body increases, these vessels passively dilate so that a major portion of the blood from the upper body is translocated into the lower vessels. Because the heart cannot pump unless blood returns to it, the greater the quantity of blood “pooled” in this way in the lower body, the less is available for the cardiac output.
هنگامیکه یک خلبان در معرض G مثبت قرار میگیرد، خون به سمت پایین ترین قسمت بدن سانتریفیوژ میشود. بنابراین، اگر نیروی شتاب گریز از مرکز 5+ G باشد و فرد در وضعیت ایستاده بی حرکت باشد، فشار در وریدهای پا به شدت افزایش مییابد (به ≈450 میلی متر جیوه). در حالت نشسته، فشار نزدیک به 300 میلی متر جیوه میشود. علاوه بر این، با افزایش فشار در رگهای پایین تنه، این رگها بطور غیرفعال گشاد میشوند به طوری که بخش عمدهای از خون از قسمت بالایی بدن به رگهای تحتانی منتقل میشود. از آنجایی که قلب نمیتواند تا زمانی که خون به آن بازگردد، پمپاژ کند، هر چه مقدار خونی که به این ترتیب در قسمت پایینی بدن جمع میشود بیشتر باشد، برای برون ده قلبی کمتر در دسترس است.
Figure 44-3 shows the changes in systolic and diastolic arterial pressures (top and bottom curves, respectively) in the upper body when a centrifugal acceleratory force of +3.3 G is suddenly applied to a sitting person. Note that both these pressures fall below 22 mm Hg for the first few seconds after the acceleration begins but then return to a systolic pressure of about 55 mm Hg and a diastolic pressure of 20 mm Hg within another 10 to 15 seconds. This secondary recovery is caused mainly by activation of the baroreceptor reflexes.
شکل 44-3 تغییرات فشار شریانی سیستولیک و دیاستولیک (به ترتیب منحنیهای بالا و پایین) در قسمت فوقانی بدن را نشان میدهد، هنگامیکه یک نیروی شتاب گریز از مرکز 3.3+ G به طور ناگهانی به یک فرد نشسته اعمال میشود. توجه داشته باشید که هر دو این فشارها در چند ثانیه اول پس از شروع شتاب به زیر 22 میلیمتر جیوه میرسند، اما در عرض 10 تا 15 ثانیه دیگر به فشار سیستولیک حدود 55 میلیمتر جیوه و فشار دیاستولیک 20 میلیمتر جیوه برمیگردند. این بهبود ثانویه عمدتاً به دلیل فعال شدن رفلکسهای بارورسپتور ایجاد میشود.
Acceleration greater than 4 to 6 G causes “blackout” of vision within a few seconds and unconsciousness shortly thereafter. If this great degree of acceleration is continued, the person will die.
شتاب بیشتر از 4 تا 6 گیگ باعث “سیاهی” دید در عرض چند ثانیه و بیهوشی در مدت کوتاهی پس از آن میشود. اگر این درجه شتاب زیاد ادامه یابد، فرد میمیرد.

Figure 44-3. Changes in systolic (top of curve) and diastolic (bottom of curve) arterial pressures after abrupt and continuing exposure of a sitting person to an acceleratory force from top to bottom of 3.3 G. (Data from Martin EE, Henry JP: Effects of time and temperature upon tolerance to positive acceleration. J Aviation Med 22:382, 1951.)
شکل 44-3. تغییرات فشار شریانی سیستولیک (بالای منحنی) و دیاستولیک (پایین منحنی) پس از قرار گرفتن ناگهانی و مداوم یک فرد نشسته در معرض نیروی شتاب دهنده از بالا به پایین 3.3 G. (دادهها از Martin EE، Henry JP: اثرات زمان و دما بر تحمل شتاب مثبت .
Effects on the Vertebrae. Extremely high acceleratory forces for even a fraction of a second can fracture the vertebrae. The degree of positive acceleration that the average person can withstand in the sitting position before vertebral fracture occurs is about 20 G.
اثرات روی مهرهها. نیروهای شتاب بسیار زیاد حتی برای کسری از ثانیه میتواند باعث شکستگی مهرهها شود. درجه شتاب مثبتی که یک فرد معمولی میتواند در حالت نشسته قبل از وقوع شکستگی مهره تحمل کند، حدود 20 گرم است.
Negative G. The effects of negative G on the body are less dramatic acutely but possibly more damaging permanently than the effects of positive G. An aviator can usually go through outside loops up to negative acceleratory forces of -4 to -5 G without causing permanent harm, although causing intense momentary hyperemia of the head. Occasionally, psychotic disturbances lasting for 15 to 20 minutes occur as a result of brain edema.
منفی G. اثرات G منفی بر بدن به صورت حاد کمتر اما احتمالاً آسیب دائمیبیشتری نسبت به اثرات G مثبت دارد. یک هوانورد معمولاً میتواند از حلقههای بیرونی تا نیروهای شتاب منفی 4- تا 5-G بدون ایجاد آسیب دائمیعبور کند، اگرچه باعث پرخونی شدید لحظه ای سر میشود. گاهی اوقات، اختلالات روان پریشی به مدت 15 تا 20 دقیقه در نتیجه ادم مغز رخ میدهد.
Occasionally, negative G forces can be so great (e.g., -20 G), and centrifugation of the blood into the head is so great, that the cerebral blood pressure reaches 300 to 400 mm Hg, sometimes causing small vessels on the surface of the head and in the brain to rupture. However, the vessels inside the cranium show less tendency for rupture than would be expected for the following reason. The cerebrospinal fluid is centrifuged toward the head at the same time that blood is centrifuged toward the cranial vessels, and the greatly increased pressure of the cerebrospinal fluid acts as a cushioning buffer on the outside of the brain to prevent intracerebral vascular rupture.
گاهی اوقات، نیروهای منفی G میتوانند به قدری زیاد باشند (مثلاً 20- گرم)، و سانتریفیوژ خون به داخل سر آنقدر زیاد است که فشار خون مغزی به 300 تا 400 میلی متر جیوه میرسد و گاهی باعث پارگی عروق کوچک در سطح سر و مغز میشود. با این حال، عروق داخل جمجمه تمایل کمتری برای پارگی از آنچه که به دلایل زیر انتظار میرود نشان میدهند. همزمان با سانتریفیوژ شدن خون به سمت عروق جمجمه، مایع مغزی نخاعی به سمت سر سانتریفیوژ میشود و فشار زیاد مایع مغزی نخاعی به عنوان یک بافر بالشتکی در قسمت بیرونی مغز عمل میکند تا از پارگی عروق داخل مغزی جلوگیری کند.
Because the eyes are not protected by the cranium, in- tense hyperemia occurs in them during strong negative G. As a result, the eyes often become temporarily blinded with what is called redout.
از آنجایی که چشمها توسط جمجمه محافظت نمیشوند، پرخونی شدید در آنها در هنگام G منفی شدید رخ میدهد. در نتیجه، چشمها اغلب بهطور موقت کور میشوند که به آن قرمزی میگویند.
Protection of the Body Against Centrifugal Acceleratory Forces. Specific procedures and apparatus have been developed to protect aviators against the circulatory col- lapse that might occur during positive G. First, if the aviator tightens his or her abdominal muscles to an extreme degree and leans forward to compress the abdomen, some of the pooling of blood in the large vessels of the abdomen can be prevented, delaying the onset of blackout. Also, special “anti-G” suits have been developed to prevent pooling of blood in the lower abdomen and legs. The simplest of these applies positive pressure to the legs and abdomen by inflating compression bags as the G force increases.
محافظت از بدن در برابر نیروهای شتاب دهنده گریز از مرکز. روشها و دستگاههای خاصی برای محافظت از هوانوردان در برابر فروپاشی گردش خونی که ممکن است در حین G مثبت رخ دهد ایجاد شده است. اولاً، اگر هوانورد ماهیچههای شکم خود را تا حد زیادی منقبض کند و برای فشردهکردن شکم به جلو خم شود، میتوان از تجمع خون در رگهای بزرگ شکم جلوگیری کرد. همچنین، لباسهای ویژه «آنتی جی» برای جلوگیری از تجمع خون در قسمت تحتانی شکم و پاها ساخته شده است. ساده ترین آنها با افزایش نیروی G با باد کردن کیسههای فشاری به پاها و شکم فشار مثبت وارد میکند.
Theoretically, a pilot submerged in a tank or suit of water might experience little effect of G forces on the circulation because the pressures developed in the water pressing on the outside of the body during centrifugal acceleration would almost exactly balance the forces acting in the body. However, the presence of air in the lungs still allows for dis- placement of the heart, lung tissues, and diaphragm into seriously abnormal positions despite submersion in water. Therefore, even if this procedure were used, the limit of safety almost certainly would still be less than 10 G.
از نظر تئوری، یک خلبان غوطه ور در یک مخزن یا لباس آب ممکن است تأثیر کمیاز نیروهای G بر روی گردش خون را تجربه کند زیرا فشارهای ایجاد شده در فشار آب در خارج از بدن در طول شتاب گریز از مرکز تقریباً دقیقاً نیروهای وارد شده در بدن را متعادل میکند. با این حال، وجود هوا در ریهها همچنان امکان جابجایی قلب، بافتهای ریه و دیافراگم را در موقعیتهای غیرعادی جدی علیرغم غوطهور شدن در آب فراهم میکند. بنابراین، حتی اگر از این روش استفاده شود، حد ایمنی تقریباً به طور قطع کمتر از 10 G خواهد بود.
Effects of Linear Acceleratory Forces on the Body
Acceleratory Forces in Space Travel. Unlike an airplane, a spacecraft cannot make rapid turns, and therefore centrifugal acceleration is of little importance except when the spacecraft goes into abnormal gyrations. However, blast-off acceleration and landing deceleration can be tremendous; both are types of linear acceleration, with one being positive and the other negative.
اثرات نیروهای شتاب دهنده خطی بر بدن
نیروهای شتاب دهنده در سفرهای فضایی. برخلاف هواپیما، فضاپیما نمیتواند چرخشهای سریع انجام دهد و بنابراین شتاب گریز از مرکز اهمیت کمیدارد مگر زمانی که فضاپیما در چرخشهای غیرعادی قرار میگیرد. با این حال، شتاب انفجار و کاهش سرعت فرود میتواند فوق العاده باشد. هر دو نوع شتاب خطی هستند که یکی مثبت و دیگری منفی است.
Figure 44-4 shows an approximate profile of acceleration during blastoff in a three-stage spacecraft, demonstrating that the first-stage booster causes acceleration as high as 9 G and the second-stage booster as high as 8 G. In the standing position, the human body could not with- stand this much acceleration, but in a semireclining posi- tion transverse to the axis of acceleration, this amount of acceleration can be withstood easily, despite the fact that the acceleratory forces continue for as long as several minutes at a time. Therefore, the reason for the reclining seats used by astronauts can be understood.
شکل 44-4 نمایه تقریبی شتاب را در حین انفجار در یک فضاپیمای سه مرحله ای نشان میدهد که نشان میدهد تقویت کننده مرحله اول شتابی تا 9G و تقویت کننده مرحله دوم تا 8G را نشان میدهد. شتاب، این میزان شتاب را میتوان به راحتی تحمل کرد، علیرغم این واقعیت که نیروهای شتاب تا چند دقیقه در یک زمان ادامه دارند. بنابراین دلیل استفاده از صندلیهای درازکش توسط فضانوردان را میتوان فهمید.
Problems also occur during deceleration when the spacecraft re-enters the atmosphere. A person traveling at Mach 1 (the speed of sound and of fast airplanes) can be safely decelerated in a distance of about 0.12 mile, whereas a person traveling at a speed of Mach 100 (a speed possible in interplanetary space travel) would require a distance of about 10,000 miles for safe deceleration. The principal reason for this difference is that the total amount of energy that must be dispelled during deceleration is proportional to the square of the velocity, which alone increases the required distance for decelerations between Mach 1 versus Mach 100 by about 10,000-fold. Therefore, deceleration must be accomplished much more slowly from a high velocity than from a lower velocity.
در هنگام کاهش سرعت، زمانی که فضاپیما دوباره وارد جو میشود، مشکلاتی نیز رخ میدهد. شخصی که با 1 ماخ (سرعت صوت و هواپیماهای سریع) سفر میکند، میتواند به طور ایمن در مسافتی حدود 0.12 مایل کاهش یابد، در حالی که شخصی که با سرعت 100 ماخ (سرعتی که در سفر فضایی بین سیاره ای ممکن است) سفر میکند، برای کاهش سرعت مطمئن به مسافتی در حدود 10000 مایل نیاز دارد. دلیل اصلی این تفاوت این است که مقدار کل انرژی که باید در حین کاهش سرعت دفع شود، متناسب با مجذور سرعت است، که به تنهایی فاصله لازم برای کاهش سرعت بین 1 ماخ در مقابل 100 ماخ را حدود 10000 برابر افزایش میدهد. بنابراین، کاهش سرعت باید از سرعت بالا بسیار کندتر از سرعت پایین تر انجام شود.
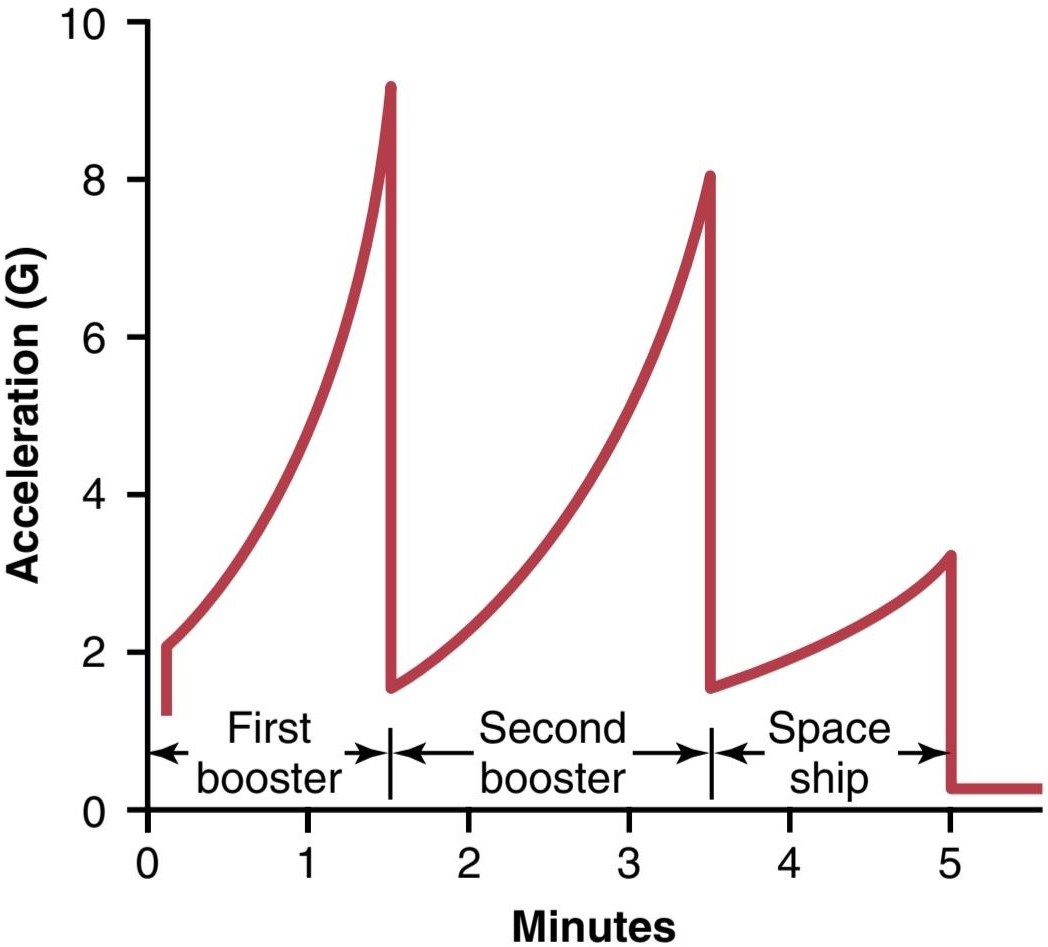
Figure 44-4. Acceleratory forces during takeoff of a spacecraft.
شکل 44-4. نیروهای شتاب دهنده در هنگام برخاستن یک فضاپیما.
Deceleratory Forces Associated With Parachute Jumps.
When the parachuting aviator leaves the airplane, the velocity of fall is at first exactly 0 feet/sec. However, because of the acceleratory force of gravity, within 1 second the velocity of fall is 32 feet/sec (if there is no air resistance), in 2 seconds it is 64 feet/sec, and so on. As the velocity of fall increases, the air resistance tending to slow the fall also icreases. Finally, the deceleratory force of the air resistance exactly balances the acceleratory force of gravity, so after falling for about 12 seconds, the person will be falling at a terminal velocity of 109 to 119 miles/ hour (175 feet/sec). If the parachutist has already reached terminal velocity be- fore opening the parachute, an “opening shock load” of up to 1200 pounds could occur on the parachute shrouds.
نیروهای کند کننده مرتبط با پرش چتر نجات.
هنگامیکه هوانورد چترباز هواپیما را ترک میکند، سرعت سقوط در ابتدا دقیقاً 0 فوت در ثانیه است. با این حال، به دلیل نیروی شتاب دهنده گرانش، در عرض 1 ثانیه سرعت سقوط 32 فوت بر ثانیه (در صورت عدم مقاومت هوا)، در 2 ثانیه 64 فوت در ثانیه و غیره است. با افزایش سرعت سقوط، مقاومت هوا که تمایل به کاهش سقوط دارد نیز افزایش مییابد. در نهایت، نیروی کند کننده مقاومت هوا دقیقاً نیروی شتاب دهنده گرانش را متعادل میکند، بنابراین پس از سقوط برای حدود 12 ثانیه، فرد با سرعت نهایی 109 تا 119 مایل در ساعت (175 فوت بر ثانیه) در حال سقوط خواهد بود. اگر چترباز قبل از باز کردن چتر به سرعت نهایی رسیده باشد، ممکن است یک “بار شوک باز شدن” تا 1200 پوند روی پوشش چتر رخ دهد.
The usual-sized parachute slows the fall of the parachutist to about one ninth the terminal velocity. In other words, the speed of landing is about 20 feet/sec, and the force of impact against the earth is 1/81, the impact force without a parachute. Even so, the force of impact is still great enough to cause considerable damage to the body unless the parachutist is properly trained in landing. Actually, the force of impact with the earth is about the same as that which would be experienced by jumping without a parachute from a height of about 6 feet. Unless forewarned, the parachutist will be tricked by her or his senses into striking the earth with extended legs, and this position, on landing, will result in tremendous deceleratory forces along the skeletal axis of the body, resulting in fracture of his pelvis, vertebrae, or leg. Consequently, the trained parachutist strikes the earth with knees bent but muscles taut to cushion the shock of landing.
چتر نجات با اندازه معمولی سقوط چترباز را تا حدود یک نهم سرعت نهایی کاهش میدهد. به عبارت دیگر، سرعت فرود حدود 20 فوت در ثانیه و نیروی برخورد به زمین 1/81 است، نیروی ضربه بدون چتر نجات. با این حال، نیروی ضربه همچنان به اندازه ای زیاد است که آسیب قابل توجهی به بدن وارد کند، مگر اینکه چترباز به درستی برای فرود آموزش دیده باشد. در واقع، نیروی برخورد با زمین تقریباً همان نیرویی است که با پرش بدون چتر نجات از ارتفاع حدود 6 فوتی تجربه میشود. اگر چترباز از قبل هشدار داده نشود، توسط حواس او فریب داده میشود تا با پاهای کشیده به زمین ضربه بزند و این وضعیت در هنگام فرود منجر به ایجاد نیروهای شتاب دهنده شدید در امتداد محور اسکلتی بدن و در نتیجه شکستگی لگن، مهرهها یا ساق پا میشود. در نتیجه، چترباز آموزش دیده با زانوهای خم شده اما ماهیچههای کشیده شده به زمین ضربه میزند تا شوک فرود را کاهش دهد.
“Artificial Climate” in the Sealed Spacecraft
Because there is no atmosphere in outer space, an artificial atmosphere and climate must be produced in a spacecraft. Most importantly, the O2 concentration must remain high enough and the CO2 concentration low enough to prevent suffocation. In some earlier space missions, a capsule atmosphere containing pure O2 at about 260 mm Hg pressure was used but, in modern space travel, gases about equal to those in normal air are used, with four times as much nitro- gen as O2 and a total pressure of 760 mm Hg. The presence of nitrogen in the mixture greatly diminishes the likelihood of fire and explosion. It also protects against development of local patches of lung atelectasis that often occur when breathing pure O2 because O2 is absorbed rapidly when small bronchi are temporarily blocked by mucous plugs.
“اقلیم مصنوعی” در فضاپیمای مهر و موم شده
از آنجایی که در فضای بیرونی جو وجود ندارد، جو و آب و هوای مصنوعی باید در یک فضاپیما تولید شود. مهمتر از همه، غلظت O2 باید به اندازه کافی بالا و غلظت CO2 به اندازه کافی پایین باشد تا از خفگی جلوگیری شود. در برخی از ماموریتهای فضایی قبلی، از جو کپسولی حاوی O2 خالص با فشار حدود 260 میلیمتر جیوه استفاده میشد، اما در سفرهای فضایی مدرن، گازهایی تقریباً برابر با گازهای موجود در هوای معمولی با چهار برابر نیتروژن O2 و فشار کل 760 میلیمتر جیوه استفاده میشد. وجود نیتروژن در مخلوط احتمال آتش سوزی و انفجار را تا حد زیادی کاهش میدهد. همچنین از ایجاد تکههای موضعی آتلکتازی ریه که اغلب هنگام تنفس O2 خالص رخ میدهند، محافظت میکند، زیرا O2 به سرعت جذب میشود که برونشهای کوچک به طور موقت توسط پلاگهای مخاطی مسدود شوند.
For space travel lasting more than several months, it is impractical to carry along an adequate O2 supply. For this reason, recycling techniques have been proposed to use the same O2 over and over again. Some recycling processes de- pend on purely physical procedures, such as electrolysis of water to release O2. Others depend on biological methods, such as use of algae with their large store of chlorophyll to release O2 from CO2 by the process of photosynthesis. A completely satisfactory system for recycling has yet to be achieved.
برای سفرهای فضایی که بیش از چند ماه طول میکشد، حمل یک منبع O2 کافی غیرعملی است. به همین دلیل، تکنیکهای بازیافت برای استفاده مکرر از O2 یکسان پیشنهاد شده است. برخی از فرآیندهای بازیافت به روشهای صرفاً فیزیکی مانند الکترولیز آب برای آزادسازی O2 بستگی دارد. برخی دیگر به روشهای بیولوژیکی مانند استفاده از جلبکها با ذخیره کلروفیل بزرگشان برای آزادسازی O2 از CO2 توسط فرآیند فتوسنتز وابسته هستند. هنوز یک سیستم کاملاً رضایت بخش برای بازیافت به دست نیامده است.
Weightlessness (Microgravity) in Space
A person in an orbiting satellite or a nonpropelled spacecraft experiences weightlessness, or a state of near- zero G force, sometimes called microgravity. That is, the person is not drawn toward the bottom, sides, or top of the spacecraft but simply floats inside its chambers. The cause of this weightlessness is not failure of gravity to pull on the body because gravity from any nearby heavenly body is still active. However, the gravity acts on the spacecraft and the person at the same time so that both are pulled with exactly the same acceleratory forces and in the same direction. For this reason, the person simply is not attracted toward any specific wall of the spacecraft.
بی وزنی (میکروگرانش) در فضا
فردی که در یک ماهواره در حال گردش یا یک فضاپیمای بدون پیشرانه است، بی وزنی یا حالتی از نیروی نزدیک به صفر G را تجربه میکند که گاهی اوقات ریزگرانش نامیده میشود. به این معنا که فرد به سمت پایین، طرفین یا بالای فضاپیما کشیده نمیشود، بلکه به سادگی در داخل اتاقک آن شناور میشود. علت این بی وزنی، ناتوانی گرانش در کشیدن بدن نیست، زیرا جاذبه از هر جسم آسمانی نزدیک هنوز فعال است. با این حال، گرانش به طور همزمان بر روی فضاپیما و شخص اثر میگذارد به طوری که هر دو دقیقاً با نیروهای شتابی یکسان و در یک جهت کشیده میشوند. به همین دلیل، فرد به سادگی به سمت هیچ دیوار خاصی از فضاپیما جذب نمیشود.
Physiological Challenges of Weightlessness (Microgravity). The physiological challenges of weightlessness have not proved to be of much significance as long as the period of weightlessness is not too long. Most of the problems that do occur are related to three effects of the weight- lessness: (1) motion sickness during the first few days of travel; (2) translocation of fluids within the body because of failure of gravity to cause normal hydrostatic pressures; and (3) diminished physical activity because no strength of muscle contraction is required to oppose the force of gravity.
چالشهای فیزیولوژیکی بی وزنی (میکرو گرانش). چالشهای فیزیولوژیکی بی وزنی تا زمانی که دوره بی وزنی خیلی طولانی نباشد، اهمیت چندانی ندارند. بسیاری از مشکلاتی که رخ میدهد به سه اثر کاهش وزن مربوط میشود: (1) بیماری حرکت در چند روز اول سفر. (2) جابجایی مایعات در بدن به دلیل ناتوانی گرانش در ایجاد فشارهای هیدرواستاتیک طبیعی. و (3) کاهش فعالیت بدنی زیرا هیچ قدرت انقباض عضلانی برای مقابله با نیروی گرانش مورد نیاز نیست.
Almost 50% of astronauts experience motion sickness, with nausea and sometimes vomiting, during the first 2 to 5 days of space travel. This motion sickness probably results from an unfamiliar pattern of motion signals arriving in the equilibrium centers of the brain and, at the same time, lack of gravitational signals.
تقریباً 50 درصد فضانوردان در طی 2 تا 5 روز اول سفر فضایی دچار بیماری حرکتی همراه با حالت تهوع و گاهی استفراغ میشوند. این بیماری حرکتی احتمالاً ناشی از الگوی ناآشنا از سیگنالهای حرکتی است که به مراکز تعادلی مغز میرسند و در عین حال، فقدان سیگنالهای گرانشی.
The observed effects of a prolonged stay in space are the following: (1) decrease in blood volume; (2) de- crease in red blood cell mass; (3) decrease in muscle strength and work capacity; (4) decrease in maximum cardiac output; and (5) loss of calcium and phosphate from the bones, as well as loss of bone mass. Most of these same effects also occur in people who lie in bed for an extended period. For this reason, exercise pro- grams are carried out by astronauts during prolonged space missions.
اثرات مشاهده شده از ماندن طولانی مدت در فضا به شرح زیر است: (1) کاهش حجم خون. (2) کاهش توده گلبول قرمز. (3) کاهش قدرت عضلانی و ظرفیت کار؛ (4) کاهش در حداکثر برون ده قلبی. و (5) از دست دادن کلسیم و فسفات از استخوانها، و همچنین از دست دادن توده استخوانی. بیشتر این اثرات مشابه در افرادی که برای مدت طولانی در رختخواب میخوابند نیز رخ میدهد. به همین دلیل، برنامههای ورزشی توسط فضانوردان در طول ماموریتهای فضایی طولانی مدت انجام میشود.
In previous space laboratory expeditions, in which the exercise program was less vigorous, the astronauts had severely decreased work capacities for the first few days after returning to Earth. They also tended to faint (and still do, to some extent) when they stood up during the first day or so after return to gravity because of diminished blood volume and diminished responses of the arterial pressure control mechanisms.
در سفرهای آزمایشگاهی فضایی قبلی، که در آن برنامه تمرینی از شدت کمتری برخوردار بود، فضانوردان در چند روز اول پس از بازگشت به زمین، به شدت ظرفیت کاری خود را کاهش داده بودند. آنها همچنین به دلیل کاهش حجم خون و کاهش پاسخهای مکانیسمهای کنترل فشار شریانی، هنگامیکه در طول روز اول یا بیشتر پس از بازگشت به گرانش ایستادند، تمایل به غش داشتند (و هنوز هم تا حدی دارند).
Cardiovascular, Muscle, and Bone “Deconditioning” During Prolonged Exposure to Weightlessness. During very long space flights and prolonged exposure to microgravity, gradual “deconditioning” effects occur on the cardiovascular system, skeletal muscles, and bone, despite rigorous exercise during the flight. Studies of astronauts on space flights lasting several months have shown that they may lose as much 1.0% of their bone mass each month, even though they continue to exercise. Substantial atrophy of cardiac and skeletal muscles also occurs during prolonged exposure to a microgravity environment.
قلب و عروق، ماهیچهها و استخوانها در طی قرار گرفتن طولانی مدت در معرض بی وزنی. در طول پروازهای فضایی بسیار طولانی و قرار گرفتن طولانیمدت در معرض گرانش میکرو، اثرات تدریجی «آرامزدایی» بر روی سیستم قلبی عروقی، ماهیچههای اسکلتی و استخوان اتفاق میافتد، علیرغم ورزش شدید در طول پرواز. مطالعات فضانوردان در پروازهای فضایی چند ماهه نشان داده است که ممکن است هر ماه 1.0 درصد از توده استخوانی خود را از دست بدهند، حتی اگر به ورزش ادامه دهند. آتروفی قابل توجهی در عضلات قلبی و اسکلتی نیز در طول قرار گرفتن طولانی مدت در یک محیط ریزگرانش رخ میدهد.
One of the most serious effects is cardiovascular “deconditioning,” which includes decreased work capacity, reduced blood volume, impaired baroreceptor reflexes, and reduced orthostatic tolerance. These changes greatly limit the astronaut’s ability to stand upright or perform normal daily activities after returning to the full gravitational force of Earth.
یکی از جدیترین اثرات، «بیحالکردن» قلب و عروق است که شامل کاهش ظرفیت کار، کاهش حجم خون، اختلال در رفلکسهای گیرنده بارور و کاهش تحمل ارتواستاتیک است. این تغییرات توانایی فضانورد را برای ایستادن یا انجام فعالیتهای عادی روزانه پس از بازگشت به نیروی گرانشی کامل زمین، بسیار محدود میکند.
Astronauts returning from space flights lasting 4 to 6 months are also susceptible to bone fractures and may re- quire several weeks before they return to preflight cardio- vascular, bone, and muscle fitness. As space flights become longer in preparation for possible human exploration of other planets, such as Mars, the effects of prolonged micro- gravity could pose a very serious threat to astronauts after they land, especially in the event of an emergency landing. Therefore, considerable research effort has been directed toward developing countermeasures, in addition to exercise, that can prevent or more effectively attenuate these changes. One such countermeasure that is being tested is the application of intermittent “artificial gravity” caused by short periods (e.g., 1 hour each day) of centrifugal acceleration of the astronauts while they sit in specially designed short-arm centrifuges that create forces of up to 2 to 3 G.
فضانوردانی که از پروازهای فضایی 4 تا 6 ماه برمیگردند نیز مستعد شکستگی استخوان هستند و ممکن است چندین هفته قبل از بازگشت به آمادگی قلبی عروقی، استخوانی و عضلانی نیاز داشته باشند. از آنجایی که پروازهای فضایی برای آماده شدن برای اکتشاف احتمالی انسان در سیارات دیگر، مانند مریخ طولانی تر میشوند، اثرات میکروگرانش طولانی مدت میتواند تهدیدی بسیار جدی برای فضانوردان پس از فرود، به ویژه در صورت فرود اضطراری باشد. بنابراین، تلاشهای پژوهشی قابلتوجهی به سمت توسعه اقدامات متقابل، علاوه بر ورزش، انجام شده است که میتواند از این تغییرات جلوگیری کرده یا به طور مؤثرتری آن را کاهش دهد. یکی از این اقدامات متقابل که در حال آزمایش است، استفاده از «گرانش مصنوعی» متناوب ناشی از دورههای کوتاه (مثلاً 1 ساعت در روز) شتاب گریز از مرکز فضانوردان در حالی که آنها در سانتریفیوژهای بازوی کوتاه طراحی شده ویژه نشستهاند است که نیرویی بین 2 تا 3 گیگ را ایجاد میکند.
کلیک کنید «Bibliography: فهرست کتب مربوطه»
Bloomfield SA, Martinez DA, Boudreaux RD, Mantri AV: Microgravity stress: bone and connective tissue. Compr Physiol 6:645, 2016.
Dekker MCJ, Wilson MH, Howlett WP: Mountain neurology. Pract Neurol 2019 Jun 8. pii: practneurol-2017-001783. https://www.
doi.org/10.1136/practneurol-2017-001783.
Dunham-Snary KJ, Wu D, Sykes EA, et al: Hypoxic pulmonary va- soconstriction: from molecular mechanisms to medicine. Chest 151:181, 2017.
Hackett PH, Roach RC: High-altitude illness. N Engl J Med 345:107, 2001.
Hargens AR, Bhattacharya R, Schneider SM. Space physiology VI: ex- ercise, artificial gravity, and countermeasure development for pro- longed space flight. Eur J Appl Physiol 113:2183, 2013.
Imray C, Wright A, Subudhi A, Roach R: Acute mountain sickness: pathophysiology, prevention, and treatment. Prog Cardiovasc Dis 52:467, 2010.
Luks AM: Physiology in medicine: A physiologic approach to preven- tion and treatment of acute high-altitude illnesses. J Appl Physiol 118:509, 2015.
Moore LG: Measuring high-altitude adaptation. J Appl Physiol 123:1371, 2017.
Penaloza D, Arias-Stella J: The heart and pulmonary circulation at high altitudes: healthy highlanders and chronic mountain sickness. Circulation 115:1132, 2007.
Prabhakar NR, Semenza GL: Adaptive and maladaptive cardiorespira- tory responses to continuous and intermittent hypoxia mediated by hypoxia-inducible factors 1 and 2. Physiol Rev 92:967, 2012.
Prabhakar NR, Semenza GL: Oxygen sensing and homeostasis. Physi- ology (Bethesda) 30:340, 2015.
Prisk GK: Pulmonary circulation in extreme environments. Compr Physiol 1:319, 2011.
Swenson ER, Bärtsch P: High-altitude pulmonary edema. Compr Physiol 2:2753, 2012.
West JB: High-altitude medicine. Am J Respir Crit Care Med 186:1229, 2012.
West JB: physiological effects of chronic hypoxia. N Engl J Med 376:1965, 2017.
Wilson MH, Imray CH: The cerebral venous system and hypoxia. J Appl Physiol 120:244, 2016.
🚀 با ما همراه شوید!
تازهترین مطالب و آموزشهای مغز و اعصاب را از دست ندهید. با فالو کردن کانال تلگرام آیندهنگاران مغز، از ما حمایت کنید!


